 +91 96001 07057
 Sidharam Heart Clinic Adyar, Gandhi Nagar, Canal Bank Road, Opp.St.Louis School, Adyar, Chennai, Tamil Nadu 600020


 27 September, 2026
Why Are Indians at Higher Risk of Diabetes and Heart Disease? Is It Genetics or Lifestyle?
Understanding the role of inherited risk, abdominal obesity, food habits, physical activity and sleep in protecting your heart
By Dr. Dhamodaran K, Interventional Cardiologist, Chennai
“My father has diabetes, my mother takes medication for blood pressure, and my grandfather had a heart attack. Does that mean I will develop these problems too?”
This is a concern shared by many young adults in India.
Another question often comes up during consultations: Why do some people develop diabetes or heart disease even though they do not look overweight? And why do certain populations appear to experience these conditions more frequently than others?
When we compare countries, it is tempting to attribute these differences entirely to genetics, food habits or exercise. However, cardiovascular health is influenced by a much more complicated combination of factors.
Your genes may influence your risk, but your everyday habits play an important role in determining your long-term health.
In this article, Dr. Dhamodaran K, Interventional Cardiologist in Chennai, explains the relationship between South Asian ancestry, diabetes, abdominal obesity and cardiovascular disease. He also discusses practical steps that can help protect your heart, even when significant medical problems run in your family.
Why do Indians have a higher risk of heart disease?
Heart disease develops through a combination of inherited and acquired risk factors.
Some individuals inherit a greater tendency to develop conditions such as high cholesterol or type 2 diabetes. Others acquire risk factors through physical inactivity, smoking, poor dietary habits or excess body fat.
For South Asians, including people from India, Pakistan, Bangladesh, Sri Lanka and Nepal, research has identified a substantial burden of diabetes and premature coronary artery disease.
One important feature is that metabolic problems may appear at a relatively young age or at a lower body weight than expected.
However, this does not mean every Indian has the same cardiovascular risk, or that genetics alone explains the differences between populations.
Family history, body composition, diet, physical activity, sleep, smoking and the broader environment all matter.
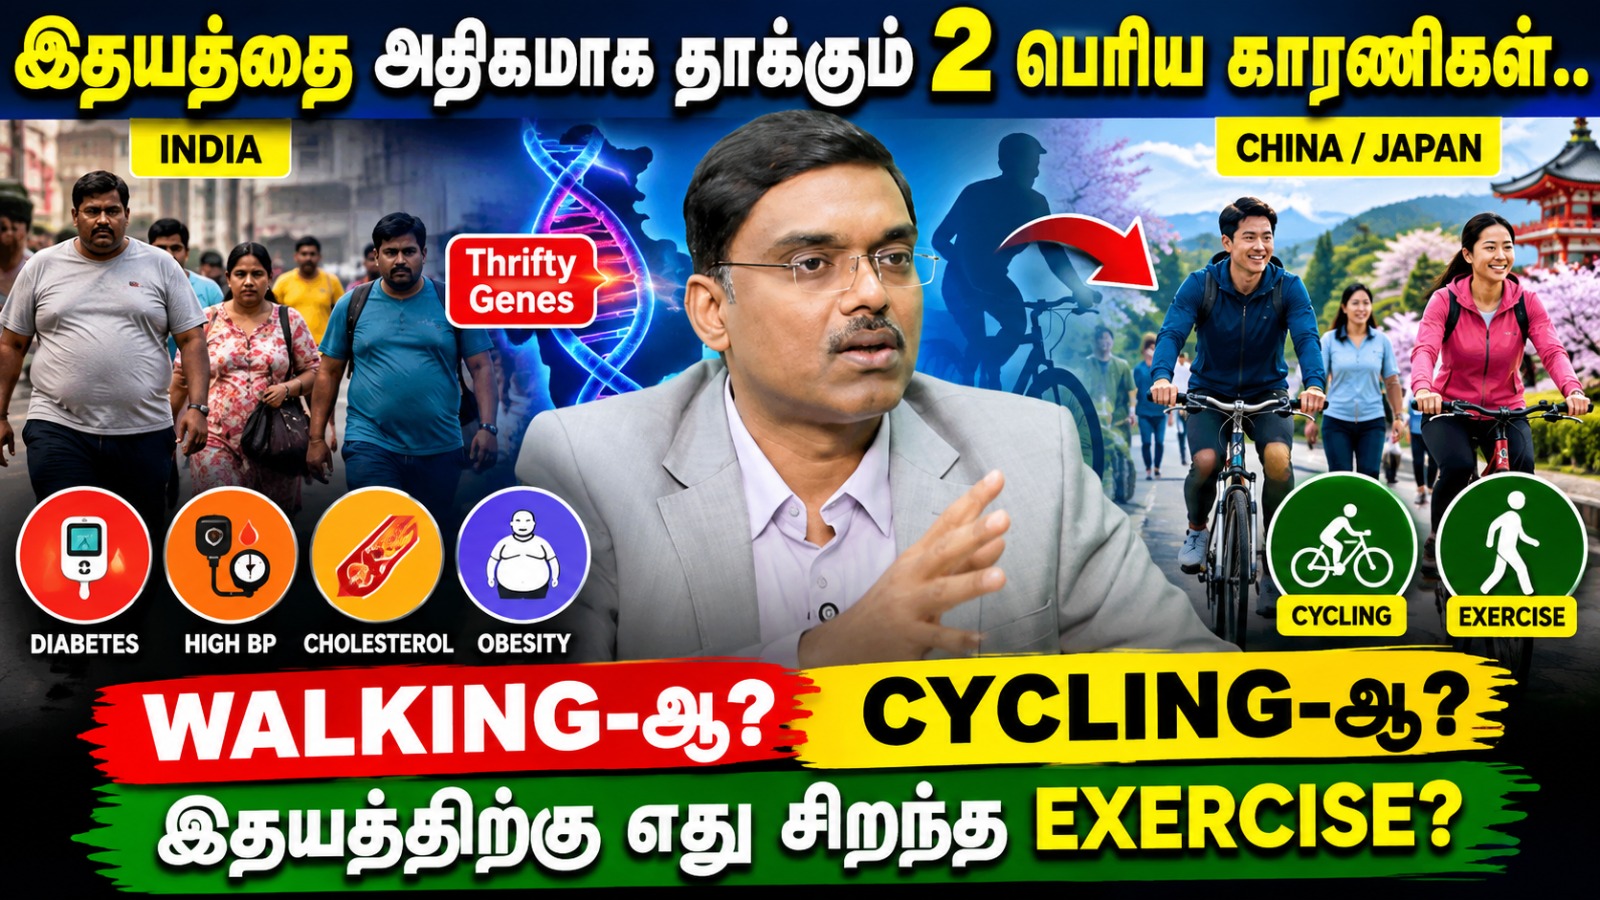
What is the thrifty gene hypothesis?
The term thrifty gene comes from an evolutionary hypothesis proposed to explain why some populations may be more susceptible to obesity and type 2 diabetes.
The idea is relatively simple.
Imagine a time when food was not consistently available. People sometimes experienced prolonged periods of scarcity followed by periods when food was plentiful.
According to the hypothesis, genetic traits that helped the body use or store energy efficiently might have provided an advantage during food shortages.
In today’s environment, where calorie-dense foods are readily available and many people spend much of the day sitting, those same tendencies could potentially contribute to metabolic problems.
This is an interesting explanation, but there is an important distinction.
The thrifty gene hypothesis has not been conclusively established, and scientists have not identified one specific set of thrifty genes responsible for heart disease in South Asians.
It is also incorrect to suggest that these genetic traits are found exclusively in India or South Asia.
Inherited susceptibility is real, but the genetic basis of obesity, diabetes and coronary artery disease is complex and involves many different variants.
Does having a genetic predisposition mean you will develop heart disease?
No.
A family history of diabetes or heart disease does not mean you are certain to develop the same condition.
Consider two people who have a similar family history.
One remains physically active, maintains an appropriate weight, does not smoke, sleeps regularly and monitors blood pressure and cholesterol.
The other is largely sedentary, frequently consumes calorie-dense processed food, smokes and leaves hypertension or diabetes untreated.
Although their inherited risks may be similar, their overall cardiovascular risk profiles can become very different.
This is why it is important not to treat genetics as an unavoidable outcome.
You may not be able to change your inherited susceptibility, but many contributing risk factors can be managed.
Why can Indians develop diabetes without looking overweight?
One of the most important concepts in metabolic health is that body weight and body fat distribution are not the same thing.
Someone may look relatively slim and still have excess fat stored around the abdominal organs.
This is called visceral fat.
Visceral fat is metabolically active and is associated with insulin resistance, abnormal blood lipids and increased cardiovascular risk.
Some South Asian populations tend to develop these metabolic abnormalities at lower body mass index (BMI) levels than certain other populations.
Consequently, looking slim does not automatically mean that your blood sugar, cholesterol and cardiovascular risk are normal.
What is central obesity?
Central obesity refers to excess fat accumulation around the abdomen.
It is often reflected by an increasing waist circumference.
A person with central obesity may have an increased risk of:
- Insulin resistance
- Type 2 diabetes
- High blood pressure
- High triglycerides
- Fatty liver disease
- Cardiovascular disease
This is one reason waist circumference can provide information that BMI alone may miss.
A proper assessment should consider both body measurements and metabolic health.
Can someone be thin and still have heart disease?
Absolutely.
Heart disease is not restricted to people who are overweight.
A person with an apparently healthy body weight may still have high LDL cholesterol, diabetes, hypertension, a strong family history or an inherited cholesterol disorder.
Some people also carry a disproportionate amount of visceral fat despite having a relatively low BMI.
This is why doctors assess the complete cardiovascular risk profile rather than judging health from physical appearance.
Why do lifestyle differences matter between countries?
People often compare India with countries such as Japan and China when discussing obesity, diabetes and physical fitness.
However, neither country has a single lifestyle shared by its entire population.
Both countries also experience obesity, diabetes and cardiovascular disease.
Nevertheless, certain everyday habits can make a meaningful difference to population health.
For example, environments that make walking, cycling and public transport convenient can help people remain physically active without needing a separate gym session.
Dietary patterns, food portions, access to healthier foods, working hours and opportunities for recreation also influence health.
Rather than assuming that everyone in another country is healthier, it is more useful to identify habits that we can adopt in our own lives.
How our daily routine has changed
Think about a typical working day.
You wake up, get ready and travel to work by car or motorbike.
You spend eight or nine hours sitting in front of a computer.
You return home through heavy traffic, have dinner and spend the rest of the evening watching television or using your phone.
By the end of the day, you may have spent nearly all your waking hours sitting.
This is a common modern routine.
Even if you do not eat excessively, prolonged inactivity can contribute to poor cardiovascular fitness, weight gain and adverse metabolic health.
The solution does not always require a complicated workout programme. Increasing movement throughout the day is an important starting point.
Is cycling particularly good for heart health?
Cycling is an excellent form of aerobic exercise for many people.
It engages large muscle groups, increases heart rate and helps improve cardiovascular endurance.
Regular cycling can support:
- Better cardiovascular fitness
- Improved blood-pressure control
- Better insulin sensitivity
- Weight management
- Muscle endurance
- General physical wellbeing
It can also be easier on the joints than high-impact activities such as running.
However, cycling is not the only effective exercise.
Walking, swimming, dancing and other forms of sustained physical activity can provide similar cardiovascular benefits.
The ideal activity is one that you can perform safely and consistently.
Do you need to cycle every day?
Not necessarily.
For most adults, a useful general goal is 150–300 minutes of moderate-intensity aerobic activity each week, along with muscle-strengthening activities on at least two days.
That may include cycling, brisk walking, swimming or a combination of different exercises.
If you currently do very little physical activity, begin with manageable sessions and increase gradually.
The aim is to build a habit that you can sustain over many years.
What about people with knee pain?
Cycling may be suitable for many patients with knee osteoarthritis because it is relatively low impact.
However, the bicycle should be adjusted appropriately, and resistance should match the individual’s ability.
Someone with severe knee pain, instability or a recent injury should obtain individual exercise advice.
Does exercise reduce the risk of diabetes?
Regular physical activity helps the muscles use glucose and can improve insulin sensitivity.
This means the body may become more efficient at regulating blood sugar.
Exercise also supports weight management and can reduce several cardiovascular risk factors.
For someone with a family history of diabetes, consistent physical activity is particularly valuable.
However, exercise does not guarantee that diabetes will never develop.
Some people have significant inherited susceptibility and may still require medication or other medical treatment.
The goal is to reduce risk and identify problems early.
Why your diet matters as much as your exercise
It is possible to exercise regularly and still have an unhealthy dietary pattern.
Likewise, eating carefully does not replace the benefits of physical activity.
Both should work together.
A heart-conscious dietary pattern generally includes plenty of vegetables, appropriate portions of whole grains, pulses, legumes, fruit, nuts and suitable protein sources.
It also limits excessive added sugar, highly processed food, trans fats and excess sodium.
Does traditional Indian food cause obesity?
Not inherently.
Traditional Indian diets include many nutritious foods.
For example, idli with sambar, dal, vegetable curries, legumes and whole grains can all form part of a balanced diet.
The problems often arise from overall calorie intake, portion size, frequent fried snacks, sugary beverages and inadequate protein or vegetables.
Preparation methods also matter.
An ordinary home-cooked meal can be quite different from a large restaurant meal containing excessive oil, salt or refined carbohydrates.
There is no need to abandon Indian cuisine to improve heart health.
Instead, pay attention to food quality, portion sizes and your overall dietary pattern.
The connection between poor sleep, diabetes and heart disease
Sleep is another important part of cardiovascular prevention.
Many working adults routinely sacrifice sleep because of late-night work, screen time or irregular schedules.
Poor sleep may affect appetite regulation, glucose metabolism and blood-pressure control.
Over time, these changes can make existing metabolic risk factors more difficult to manage.
For most adults, aiming for seven to nine hours of good-quality sleep is reasonable.
However, sleeping for eight hours does not automatically eliminate cardiovascular risk.
Someone who sleeps well but smokes, has uncontrolled diabetes or has very high LDL cholesterol still needs appropriate preventive care.
Healthy sleep is one part of a comprehensive approach.
When should Indians start checking their heart risk?
Prevention can begin in early adulthood.
You do not need to wait until your 40s or 50s to learn your blood pressure, cholesterol or blood-sugar levels.
This is especially relevant if your family has a history of premature heart disease, diabetes, high blood pressure or unusually high cholesterol.
An initial risk assessment may include blood-pressure measurement, a lipid profile, blood-sugar testing when appropriate, BMI and waist circumference.
Your doctor can decide how frequently testing should be repeated based on your age, previous results and individual risk factors.
Does everyone in their 20s need a complete heart check-up?
No.
A healthy young adult without symptoms does not automatically need a treadmill test, echocardiogram or CT coronary angiogram.
A targeted cardiovascular risk assessment is usually more appropriate.
For example, a 25-year-old whose father had a heart attack at 42 may need earlier attention to cholesterol and other inherited risk factors.
Someone with obesity and a strong family history of diabetes may benefit from earlier blood-sugar screening.
The right investigations depend on the person.
What if your cholesterol and blood sugar are normal?
Normal results are reassuring, but they do not guarantee that cardiovascular disease can never develop.
Continue maintaining healthy habits and repeat relevant measurements at intervals recommended by your doctor.
If your family history is particularly strong, your cardiologist may consider additional risk assessment.
A practical daily routine for better heart health
You do not need to transform your entire lifestyle overnight.
A more sustainable approach is to make small improvements that become permanent habits.
Start your day with a comfortable walk or cycling session if your health allows.
During working hours, avoid remaining seated continuously. Get up periodically, walk for a few minutes and use opportunities for everyday movement.
Build meals around vegetables, suitable protein and sensible portions.
Reduce sugary drinks and frequent calorie-dense snacks.
Include some resistance training to help preserve muscle strength.
Maintain a regular sleeping schedule.
If you smoke, seek support to stop.
And most importantly, follow prescribed treatment if you already have diabetes, high blood pressure or high cholesterol.
Lifestyle changes and appropriate medical treatment should complement each other—not compete with each other.
Frequently Asked Questions About Genetics, Diabetes and Heart Disease in Indians
1. Why do Indians develop heart disease at a younger age?
South Asian populations have a significant burden of premature coronary artery disease. Factors may include diabetes, abdominal obesity, abnormal cholesterol, smoking, hypertension, genetic susceptibility and lifestyle or environmental influences.
2. Is heart disease genetic in Indians?
Genetics contributes to cardiovascular risk, but heart disease is not determined by ancestry alone. Lifestyle, metabolic health, family history and environmental factors all influence individual risk.
3. What are thrifty genes?
The thrifty gene hypothesis proposes that certain inherited traits may have favoured efficient energy storage during historical periods of food scarcity. It remains a hypothesis and has not been conclusively demonstrated as the explanation for obesity or diabetes in South Asians.
4. Are thrifty genes found only in South Asians?
No. It is not scientifically established that a unique set of thrifty genes exists only in South Asians. The genetics of obesity and diabetes are complex and involve many variants across populations.
5. Does having a family history of diabetes mean I will develop diabetes?
No. Family history increases susceptibility, but it does not guarantee that you will develop the disease. Physical activity, weight management, diet, sleep and appropriate screening remain important.
6. Can a thin Indian person develop diabetes?
Yes. Some people develop insulin resistance and type 2 diabetes despite not appearing overweight. Abdominal fat distribution and inherited susceptibility can contribute.
7. Why is belly fat associated with heart disease?
Excess visceral fat is associated with insulin resistance, high triglycerides, hypertension and other metabolic abnormalities that can increase cardiovascular risk.
8. Is BMI enough to assess obesity?
Not always. BMI is useful, but it does not directly measure abdominal fat or distinguish fat from muscle. Waist circumference and other clinical measurements may provide additional information.
9. Do Asian populations have different BMI risk thresholds?
For many Asian populations, metabolic risk can occur at lower BMI values than conventional thresholds used for other populations. Your doctor should interpret BMI together with waist circumference and individual risk factors.
10. Are people in Japan and China free from obesity and heart disease?
No. Both countries have obesity, diabetes and cardiovascular disease. Population averages may differ, but health risks vary widely within each country.
11. Can cycling help prevent heart disease?
Regular cycling improves cardiovascular fitness and can help control several important risk factors. It is one useful form of exercise, but no single activity guarantees complete protection.
12. Is cycling better than walking?
Both are beneficial. Cycling may be more comfortable for some people with joint problems, while walking is easily accessible and requires no special equipment. Choose an activity that suits your health and preferences.
13. How much exercise should adults aim for?
Most adults should aim for at least 150 minutes of moderate-intensity aerobic activity per week, working toward higher amounts when appropriate, with muscle-strengthening exercise on at least two days.
14. Can exercise reverse inherited heart risk?
Exercise cannot change your genes. However, it can improve several modifiable cardiovascular risk factors and contribute meaningfully to long-term prevention.
15. Does sleeping seven to nine hours prevent heart attacks?
Adequate sleep supports cardiovascular health, but it cannot guarantee prevention. Cholesterol, diabetes, blood pressure, smoking and other risk factors still need attention.
16. Should everyone start heart screening at age 20?
Not everyone needs extensive cardiac testing at that age. However, knowing your basic risk factors in early adulthood is sensible, especially if significant cardiovascular disease or diabetes runs in your family.
17. What are the first tests I should consider?
Depending on your medical history, an initial assessment may include blood pressure, a lipid profile, blood-sugar testing, BMI and waist circumference.
18. If I exercise every day, can I still have high cholesterol?
Yes. Some people have inherited cholesterol disorders or other risk factors that are not fully controlled by exercise and diet. Medication may still be necessary.
19. Should people with diabetes consult a cardiologist?
People with diabetes should receive regular cardiovascular risk assessment as part of routine medical care. A cardiology consultation may be appropriate when there are symptoms, established cardiovascular disease or other significant risk factors.
20. What is the most important message for someone with a strong family history?
Do not assume that you are destined to develop the same disease. Learn your risk factors early, follow a sustainable lifestyle and seek appropriate medical care when needed.
Final Takeaway: Your Genes Are Only Part of the Story
If heart disease or diabetes runs in your family, it is natural to worry about your future.
But inherited susceptibility is not a prediction of what will definitely happen.
The way your risk develops over time is influenced by several factors, including your metabolic health, physical activity, diet, sleep and medical treatment.
South Asians may develop certain cardiovascular and metabolic risk factors at a lower body weight or younger age, making early awareness particularly important.
However, genetics should never become a reason to give up on prevention.
Build regular physical activity into your day. Choose balanced meals. Maintain a healthy waist circumference. Sleep consistently. Avoid smoking. Know your blood pressure, blood sugar and cholesterol.
You cannot choose your family history, but you can take meaningful steps to protect your cardiovascular health.
Consult Dr. Dhamodaran K
Dr. Dhamodaran K
MBBS, DM (Cardiology), FNB, FESC, FSCAI
Interventional Cardiologist, Chennai
Sidharam Multispeciality Clinic
Old No. 2, New No. 4
Canal Bank Road, Gandhi Nagar
Adyar, Chennai – 600020
Tamil Nadu
Appointments: +91 96001 07057
Apollo Hospitals
Greams Road, Chennai, Tamil Nadu
For consultations related to:
- Preventive cardiovascular risk assessment
- Family history of premature heart disease
- Cholesterol and coronary artery disease
- Heart symptoms and interventional cardiology evaluation
Medical disclaimer: This article is intended for general educational purposes only and should not replace individual medical advice. Cardiovascular and diabetes risks vary according to medical history, family history, symptoms and other factors. Consult a qualified healthcare professional for an individual assessment. Seek emergency medical care for severe chest discomfort, sudden breathlessness, fainting or other symptoms suggestive of a heart attack.